
Last Updated: October 25, 2026
Quick Summary
Air ambulance patient eligibility criteria come down to whether the patient needs medical care in transit that only an aircraft crew can provide, judged across seven criteria: a time-sensitive condition, distance and access, clinical need versus coverage, prior authorization, medical condition type, patient stability, and documentation. Clinical eligibility and insurance coverage are two separate decisions made by different people, so a patient can meet every medical criterion and still face a denied claim.
- A 2022 study found a median air medical transport patient age of 37, with 59% reporting no other health conditions.
- Most air ambulances cruise at cabin altitudes equivalent to 6,000 to 8,000 feet, which can drop oxygen saturation.
- Emergency transport often skips prior approval, but non-emergency interfacility transfers usually cannot.
- Get the prior authorization number in writing before the aircraft is booked, not just a verbal okay.
- A stabilize and reassess window of 30 to 60 minutes often decides whether a flight proceeds.
Table of Contents
- Who Qualifies for Air Ambulance Transport: The 7 Criteria That Decide
- Criterion 1: A Time-Sensitive Emergency Medical Condition
- Criterion 2: Distance and Access to Care
- Clinical Eligibility vs Insurance Coverage: Two Separate Decisions
- Air Ambulance Insurance Coverage Criteria and Prior Authorization
- Medical Conditions That May Require Air Transport
- Patient Stability and Flight Suitability: When Flying Is Too Risky
- Medical Escort Flight Eligibility for Patients Who Can Fly Commercially
- Commercial Stretcher Flight Requirements and Onboard Equipment
- Documenting Medical Necessity and Arranging Your Transfer
- Frequently Asked Questions
Who Qualifies for Air Ambulance Transport: The 7 Criteria That Decide
Air ambulance patient eligibility criteria come down to one question: does this patient need medical care in transit that only an aircraft crew can provide? A 2022 study of patients requiring air medical transport found a median age of 37 years, with 59% reporting no other health conditions (patient characteristics in air medical transport(https://pmc.ncbi.nlm.nih.gov/articles/PMC8904089/)). In other words, air transport is not just for the very old or the very sick.
Here is each criterion, so families, case managers, and referring clinicians can judge a case in minutes:
| Criterion | What It Asks | Who Decides |
|---|---|---|
| 1. Time-sensitive condition | Will delay cause harm? | Treating clinician |
| 2. Distance and access | Is ground transport too slow or unavailable? | Transport coordinator |
| 3. Clinical vs coverage | Is the flight needed AND payable? | Clinician and payer |
| 4. Prior authorization | Has the plan approved it? | Insurance plan |
| 5. Medical condition type | Does the diagnosis fit air transport? | Treating clinician |
| 6. Patient stability | Can the patient tolerate altitude and cabin stress? | Flight medical team |
| 7. Documentation | Is medical necessity recorded? | Referring facility |
Criterion 1: A Time-Sensitive Emergency Medical Condition
The first criterion: the patient needs care fast, and the clock itself is a risk.
Distance changes the math here. A 2026 consensus study developed a definition of air medical transport need for trauma patients that can be used for triage, though the authors say it still needs validation (consensus definition of air medical transport need(https://pubmed.ncbi.nlm.nih.gov/41712185/)).
If you are arranging critical care transport for a complex case, our guide on critical care transport explains what it covers and when it is used.
Criterion 2: Distance and Access to Care
Distance and access decide the second criterion. Air transport makes sense when the receiving facility is far away, roads are blocked, or no local hospital can provide the needed care, a rural clinic three hours from a trauma center is a classic case.
Ask two questions:
- How long would ground transport take, door to door?
- Does the receiving facility offer care the patient cannot get locally?
If ground time is long and the answer to the second question is yes, air transport is worth evaluating.
Clinical Eligibility vs Insurance Coverage: Two Separate Decisions
The most common mistake we see is treating clinical eligibility and insurance coverage as one decision. They are separate, decided by different people using different rules: a patient can meet every medical criterion and still face a denied claim, and a plan can approve a flight a clinician would not recommend. Keeping the two checklists apart avoids surprise bills and delayed transport.
The Clinical Eligibility Checklist
This checklist is for the treating clinician and the transport coordinator. It answers one question: does this patient need air transport for medical reasons?
- Time-sensitive condition: Is there a diagnosis or injury where delay could cause serious harm (e.g., stroke, heart attack, major trauma)?
- Ground transport limitation: Would ground transport take too long, or is it unavailable due to distance, roads, or weather?
- Destination need: Does the receiving facility offer care the patient cannot get locally (e.g., cath lab, trauma center, high-risk obstetrics)?
If most boxes are checked, the clinical case for air transport is strong. Document each one.
The Coverage Checklist
This checklist is for the patient, family, or case manager. It answers a different question: will the payer cover this transport under its own rules?
- Medical necessity definition: Does the plan’s definition of medical necessity match the clinical findings? (Most plans require that ground transport be contraindicated or that the level of care be medically necessary.)
- Nearest appropriate facility: Is the flight going to the closest facility that can provide the needed care? Many plans deny claims if a farther facility is chosen without justification.
- Prior authorization: For non-emergency flights, has the plan approved the transport in advance? Get the authorization number in writing.
Why the Two Checklists Diverge
A patient may be clinically eligible but not covered, or covered but not clinically eligible. A stable patient who needs a stretcher but could tolerate a commercial flight with a medical escort may not meet a plan’s definition of “air ambulance” medical necessity; conversely, a plan may approve a flight a flight surgeon deems too risky. The clinical team decides safety and need; the payer decides payment.
Before booking, ask the payer for the specific medical necessity criteria they will apply. Then map your clinical documentation to those criteria point by point. This preemptive step reduces denials.
For a deeper look at how different payers apply these rules, see our guide on whether insurance covers long distance medical transport.
Air Ambulance Insurance Coverage Criteria and Prior Authorization
Emergency transport often skips prior approval, because no one can ask permission mid-crisis. Non-emergency interfacility transfer usually cannot.
For a deeper look at what Medicare, Medicaid, and private plans pay, read our guide on whether insurance covers long distance medical transport.
Watch out: families often assume a verbal “okay” from a plan is approval. Get the authorization number in writing before the aircraft is booked.
Medical Conditions That May Require Air Transport
Certain conditions show up again and again in air transport requests, the ones where speed and specialized support change outcomes:
- Traumatic injury from a crash or fall, especially with head or internal injuries
- Heart attack needing a cath lab that is far away
- Stroke within the treatment window for clot removal
This list is not a rulebook. A patient with none of these conditions can still qualify if the time-and-access test points to air. A patient with one of them may not qualify if the flight adds risk without benefit.
Patient Stability and Flight Suitability: When Flying Is Too Risky
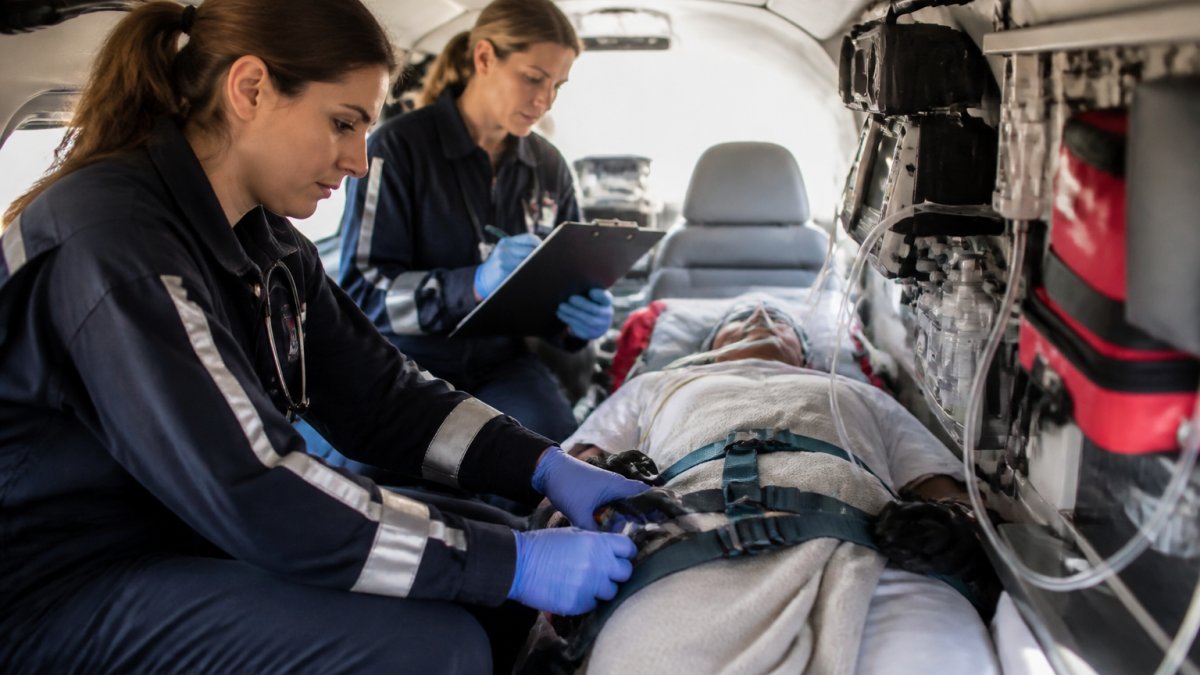
Patient stability decides whether a flight is safe, not just useful. Altitude lowers oxygen levels and cabin pressure shifts, so a patient stable on the ground can become unstable in the air.
Aircraft-Specific Constraints
Not every aircraft can safely transport every patient. The flight medical team must match the patient’s condition to the aircraft’s capabilities:
- Cabin altitude: Most air ambulances cruise at cabin altitudes equivalent to 6,000-8,000 feet, which can drop oxygen saturation in patients with respiratory or cardiac compromise. Fixed-wing jets can often maintain lower cabin altitudes than helicopters.
- Pressurization: Unpressurized helicopters may be limited to lower altitudes, increasing turbulence and flight time. Pressurized fixed-wing aircraft are preferred for patients with pneumothorax, recent surgery, or bowel obstruction.
- Space and equipment: A patient on multiple IV pumps, a ventilator, or an intra-aortic balloon pump may require a larger aircraft with a dedicated stretcher and mounting systems. Not all helicopters have the payload or cabin space.
The Stabilization Decision
When a patient is too unstable to fly, stabilize first, then transport. The flight team and referring clinician weigh the risk of delay against the risk of flight. Common steps include:
- Securing the airway and confirming ventilator settings
- Achieving hemodynamic stability (blood pressure and heart rate within acceptable limits)
- Draining a pneumothorax or placing a chest tube
A common pattern is a “stabilize and reassess” window of 30-60 minutes. If the patient improves, the flight proceeds. If not, ground transport or a different destination may be safer.
When Flight Is Contraindicated
Certain conditions may make air transport too risky regardless of medical need:
- Severe uncorrected hypoxemia despite high-flow oxygen
- Active seizure or agitation requiring continuous sedation that cannot be maintained in flight
- Untreated pneumothorax (risk of tension pneumothorax at altitude)
In these cases, the flight team may recommend ground transport to a closer facility for stabilization before a longer air transfer.
Do not assume a verbal clearance from a referring physician is sufficient. The flight medical team must perform its own fit-to-fly assessment, including a review of vital signs, oxygen requirements, and equipment needs.
A 2026 U.S. news report described research linking air ambulance transport to higher survival after severe injuries, but survival benefit and flight safety are separate questions (air ambulances and survival after severe injuries(https://www.usnews.com/news/health-news/articles/2026-02-06/air-ambulances-linked-to-higher-survival-after-severe-injuries)). The decision to fly must balance urgency against the patient’s ability to tolerate the journey.
Medical Escort Flight Eligibility for Patients Who Can Fly Commercially
Medical escort flight eligibility applies when a patient is stable enough for a commercial flight but needs a clinician nearby, a middle path between a full air ambulance and flying alone.
Who tends to qualify:
- Patients who can walk and sit upright without help
- Patients who need oxygen or medication monitoring in flight
- Patients recovering from surgery who are cleared to fly
Who usually does not qualify: patients on a stretcher, patients who need a ventilator, and anyone whose condition could crash mid-flight.
Our medical escort flight guide covers who qualifies, how booking works, and what to expect.
Commercial Stretcher Flight Requirements and Onboard Equipment
Commercial stretcher flight requirements cover patients who cannot sit up but do not need a full air ambulance.
Typical requirements include:
- A medical clearance letter from the treating doctor
- A stretcher fit-to-fly assessment
- Advance booking with the airline’s medical desk
Aircraft configuration matters: not every plane can take a stretcher, and the airline must confirm the layout in advance. This option costs less than a dedicated jet but runs on commercial schedules, so timing is less flexible.
For the full picture on how a stretcher on a commercial flight is arranged and equipped, see our detailed guide.
Documenting Medical Necessity and Arranging Your Transfer
Medical documentation is the last criterion, and the one that protects the patient’s wallet. Medical necessity must be recorded in writing: the diagnosis, why ground transport will not work, and why the receiving facility is the right destination.
A strong record includes:
- A letter from the treating physician stating the medical need
- Clinical notes supporting the time-sensitive nature of the case
- The receiving facility’s acceptance and bed confirmation
Once the paperwork is in order, our step-by-step guide on how to arrange an air ambulance walks through booking, what to confirm, and how to choose a provider.
Travel Care Air handles this coordination for hospitals, families, and care teams worldwide, with 24/7 service and a dedicated air ambulance jet. Our flight nurses provide ICU-level care in transit, and we keep families updated at every stage of the journey.
Frequently Asked Questions
Who qualifies for air ambulance transport?
Qualification rests on three things: a medical condition that needs time-sensitive or intensive care, a distance or access problem that makes ground transport impractical, and a patient stable enough to fly. Clinical need is only half the answer, because your payer applies its own medical-necessity and prior-authorization rules on top.
Does insurance cover an air ambulance if the patient meets medical criteria?
Not automatically. Air ambulance insurance coverage criteria are set by each plan, and meeting a clinician’s definition of need does not guarantee payment. The Federal Employee Program guideline, for example, requires prior approval for all non-emergency air ambulance transport. Emergency transports are usually assessed against medical-necessity criteria after the fact. Ask your insurer two questions before booking: what documentation they require, and whether prior authorization applies to your transport type.
Can a patient travel by commercial flight with a medical escort instead of an air ambulance?
Sometimes, yes. Medical escort flight eligibility usually requires a patient who is clinically stable, needs monitoring or assistance rather than intensive care, and can sit upright for the journey. A flight nurse escort travels on a scheduled commercial service and manages medications, oxygen and observation in transit. Patients who cannot sit upright, need a stretcher, or require critical care equipment fall under commercial stretcher flight requirements or a dedicated air ambulance instead.
What happens when a patient is too unstable to fly?
Transport is delayed until the patient is stable enough, and the receiving facility is told why. A 2022 study of patients requiring air medical transport found a median age of 37, with 59% reporting no comorbidities, which shows how varied the flying population is. In practice, the flight medical team assesses stability against altitude and cabin pressure effects. If the risk outweighs the benefit, care continues on site until the patient can travel safely.
Coordinating a transfer under pressure is hard, and the paperwork rarely waits. If you are weighing air transport for a patient, Travel Care Air can review the case, confirm flight suitability, and coordinate the medical crew, aircraft, and documentation in one place. We have done this work since 1980, with global reach and 24/7 availability. Get started with Travel Care Air and request a quote for your transfer today.
